A queue management system in hospital OPDs does one job a paper token can’t: it moves each patient through registration, the right doctor’s OPD, pharmacy, lab and billing without a separate crowded line at every step.
Ask any hospital administrator in India what happens between a patient walking in and seeing a doctor, and “queue” undersells it. There’s a registration line, a doctor-wise OPD queue, a pharmacy queue, a lab queue and a billing queue. That’s four or five separate waits stitched into one visit, and most are still run on paper tokens or a register.
This guide covers what a hospital queue system needs to do, how it works stage by stage, what to look for when buying one, and how the check-in step now connects to ABDM and the DPDP Act.
A queue management system in hospital OPDs is software that lets patients check in by QR code, kiosk or appointment, puts them in the right queue for their doctor or department, shows their live position and expected wait on their phone, alerts them when their turn is near, and logs every step with a timestamp. It replaces paper tokens and one blended OPD line.
Key Takeaways
- A hospital visit is several linked queues: registration, doctor-wise OPD, pharmacy, lab and billing. A hospital queue system has to route patients across all of them, not manage one line.
- The biggest wait-time win is usually routing, not faster doctors. A 5-minute pharmacy pickup shouldn’t wait behind a 20-minute consultation.
- In a study of 30 hospitals in Nellore, Andhra Pradesh, average OPD waits ranged from 15.5 minutes in private hospitals to 39.71 minutes in voluntary-sector hospitals, and men’s median wait was 19% lower than women’s.
- Check-in is where a patient’s ABHA ID is captured or verified. ABDM’s Digital Health Incentive Scheme (DHIS) pays facilities for ABHA-linked records, but its rates change often, so check the current terms.
- A patient’s name, phone number and visit time are personal data under the DPDP Act, 2023. The DPDP Rules, notified on 14 November 2025, phase in compliance over 18 months.
What Is a Queue Management System in a Hospital?
A queue management system in hospital settings is software that lets patients check in digitally (by QR code, kiosk or pre-booked appointment), routes them into the correct queue (a specific doctor’s OPD, pharmacy, lab or billing), tracks the live wait, and logs each stage of the visit for records and reporting.
A retail or bank queue manages one kind of wait. A hospital visit is a chain of them. A patient might register, wait for a specific doctor, walk to the pharmacy, wait again, then queue at billing. A single “take a token” system can’t represent that. A hospital queue system needs doctor-wise and department-wise routing from the start, so a patient’s place in the pharmacy queue depends on when they reach the pharmacy, not when they arrived at the hospital.
The other thing specific to healthcare is the record. Every check-in captures at least a name and phone number, and increasingly a link to the patient’s ABHA health ID. That record needs to be accurate, timestamped and collected with proper notice.
Key terms used in this guide:
- Doctor-wise and department-wise routing: automatically placing a patient in the correct sub-queue (a specific doctor’s OPD, pharmacy, lab or billing) instead of one blended line.
- ABHA ID: the Ayushman Bharat Health Account, a 14-digit health ID under the Ayushman Bharat Digital Mission (ABDM) that links a patient’s records across providers.
- DHIS: the Digital Health Incentive Scheme under ABDM, which pays health facilities for KYC-verified, ABHA-linked digital health records above a monthly baseline.
- Personal data (DPDP Act, 2023): any data about an individual who can be identified by it. A patient’s name, phone number and visit timestamp all qualify.
Where Hospital Queue Management Fits in the Patient Journey
Queue management spans four stages of a hospital visit, not just the wait at one counter. A system that only covers one stage solves a smaller problem than it appears to.
- Pre-arrival: online appointment booking, visit instructions and, where the hospital participates in ABDM, advance ABHA linkage. A patient who arrives already registered has a much faster check-in.
- Arrival: check-in by QR code, kiosk or front desk. This is where consent for data use is captured and where the patient gets a realistic wait estimate instead of silence.
- Service: doctor-wise OPD, pharmacy, lab and billing. Routing, live wait visibility and staff call-up matter most here.
- Post-visit: billing, prescription pickup and follow-up booking. This is also where the visit’s data (wait times, no-shows, service durations) becomes something the hospital can analyse instead of losing to a paper register.
Why This Matters for Hospitals in India Right Now
Three things are converging on hospital front desks in 2026: evidence that OPD waits are long and unevenly spread, ABDM incentives tied to how patients are registered, and legal duties under the DPDP Act for the data collected at check-in.
The evidence on waiting times. A study of 830 patients at 30 randomly selected hospitals in Nellore, Andhra Pradesh, found average OPD waits of 20.3 minutes in government hospitals, 15.5 minutes in private hospitals and 39.71 minutes in voluntary-sector hospitals (Sriram and Noochpoung, IJCMPH, 2018). After adjusting for other factors, men’s median wait was 19% lower than women’s. Patients arriving by ambulance waited 64% less than others, except in public hospitals. The data is from one district in 2012, but the pattern is the point: none of it shows up on a paper token system. It only becomes visible once check-in and wait times are logged.
ABDM and DHIS. Hospitals are being encouraged to create ABHA-linked patient records. Under DHIS, facilities earn incentives for KYC-verified, ABHA-linked records above a baseline of 100 a month. Under Corrigendum 7 (April to September 2026), that’s about ₹5 per OP consultation or prescription record and ₹10 per discharge summary or diagnostic report (ClaimsLens summary). The scheme has been revised seven times since January 2023, so check the official DHIS page before building projections. Because check-in is where a patient’s ABHA ID is captured or verified, the queue and ABHA linkage should be designed together.
The DPDP Act. A patient’s name and phone number collected to run a queue are personal data, and the hospital is a data fiduciary with notice and consent duties. The DPDP Rules were notified on 14 November 2025, with an 18-month phased compliance period (PIB). This is general information, not legal advice. Have your compliance or legal team review how patient data is captured and used.
Key Benefits of a Hospital Queue Management System
A queue management system in hospital OPDs shortens the time patients spend standing in corridors, gives staff a timestamped record of every visit, and turns check-in into a clean moment for consent and ABHA linkage.
- Shorter, more predictable waits. Routing a 5-minute pharmacy pickup away from a 20-minute consultation queue means the pharmacy patient doesn’t inherit someone else’s wait. It’s a structural fix, not a “hire more staff” fix.
- A record of patient flow. Every check-in, transfer and completion is timestamped, so “how long did this patient wait for Dr. X?” has a real answer.
- One check-in for queue, consent and ABHA. Digital check-in can show patients what data is collected and why, log their consent, and prompt for their ABHA ID where your systems support it.
- Visibility into access gaps. If some patient groups wait longer, logged data is the only way to see it and fix it.
- Calmer waiting areas. Patients who can wait in the cafeteria or parking area instead of a packed OPD corridor are more comfortable and easier to manage.
- Department-level reporting and less front-desk pressure. Administrators see OPD, pharmacy, lab and billing waits separately instead of one blended average, and staff field fewer “how much longer?” questions.

| Dimension | Manual Token / Register | Digital Hospital Queue |
|---|---|---|
| Department routing | One line per counter, manually managed | OPD/pharmacy/lab/billing routed automatically |
| Wait-time visibility | Anecdotal, department by department | Logged and comparable across departments |
| ABHA linkage | A separate administrative step, if done at all | Captured at the same check-in moment |
| Consent for patient data | Not collected | Captured at check-in, logged |
| Equity visibility | Invisible | Measurable (e.g., wait time by patient group) |
| ROI evidence | Anecdotal or unsourced vendor claims | Grounded in independently published research |
How a Hospital Queue Management System Works
A hospital queue system runs a four-stage flow: the patient checks in, the system routes them to the right queue, they wait with a live position and a phone alert, and each stage is logged when it’s completed.
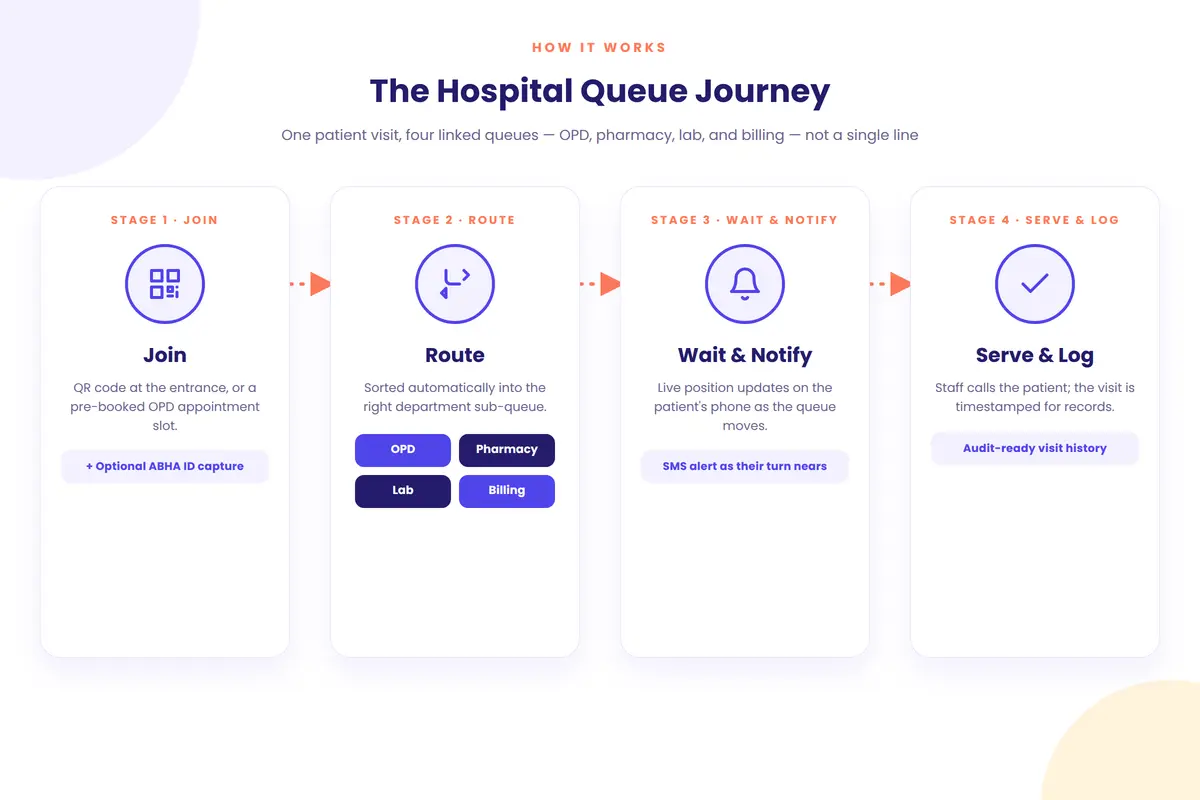
Stage 1: Join
A walk-in patient scans a QR code, checks in at a kiosk or is registered at the front desk. A patient with a booked appointment checks in the same way. They see a clear consent notice and, where the hospital participates in ABDM, are prompted to link or verify their ABHA ID. The output is a token with a queue position, an estimated wait and a logged consent record.
Stage 2: Route
The patient picks, or staff assign, the reason for the visit: a specific doctor’s OPD, pharmacy, lab or billing. The system places them in that sub-queue instead of one blended line. In Promptier, for example, each doctor or department is set up as its own queue (see how hospital queue management works).
Stage 3: Wait and Notify
The patient’s position and estimated wait update live on their phone. As their turn nears, they get a phone notification (a browser alert, SMS or WhatsApp message, depending on the system), so they don’t need to stand by the door.
Stage 4: Serve and Log
Staff or the doctor call the next token, the patient is served, and the system logs the timeline: check-in time, department, wait duration and completion time. That record feeds the hospital’s dashboard and, where relevant, ABDM reporting.
| Stage | Cadence | Owner | Typical Tooling |
|---|---|---|---|
| Join | Continuous | Patient (self-service) or front desk | QR code, kiosk, booking link, consent notice |
| Route | Automated | System | Doctor/department sub-queues |
| Wait & Notify | Continuous | System | Live position, SMS alert |
| Serve & Log | Per visit | Staff/doctor | Counter or room call-up, timestamped record |
Best Practices for Hospital Queue Management
The single most useful practice is routing by doctor and department before optimising anything else. Most long OPD waits come from blended queues, not slow individual service.
- Route by doctor, not just by department. One OPD line for every doctor in a specialty hides who is running late. A sub-queue per doctor gives each patient a realistic wait for the doctor they’re actually seeing.
- Separate quick transactions from long ones. Pharmacy, lab and billing each get their own queue, so a 5-minute pickup doesn’t wait behind a 20-minute consultation.
- Capture ABHA at check-in, not as an afterthought. Offer ABHA linkage in the same flow as joining the queue, rather than at a separate desk patients skip.
- Make consent part of check-in. Show a clear notice and log the patient’s consent, instead of collecting a phone number with no record.
- Track wait time by patient group. One overall average hides gaps. Check whether women, elderly patients or walk-ins wait longer, and find out why.
| Situation | What to do | Expected result |
| One OPD line for several doctors | Give each doctor a sub-queue | Patients see a realistic, doctor-specific wait |
| Pharmacy and billing stuck behind consultations | Give each department its own queue | Total visit time drops without adding staff |
| ABHA linkage at a separate desk | Offer it at queue check-in | Higher linkage rate, less patient friction |
| No view of wait time by patient group | Track and review it weekly | Access gaps become visible and fixable |
Common Challenges and How to Solve Them
The most common mistake is digitising the main registration desk and stopping there. Registration gets faster, but pharmacy, lab and billing stay on paper, so the patient’s total visit barely gets shorter and the project gets blamed.
Only registration gets digitised
Plan department coverage from day one, even if the rollout is phased. Commit to a date for pharmacy, lab and billing rather than leaving them “for later”.
Elderly or less digitally comfortable patients struggle with QR check-in
Keep a staffed front desk or kiosk that can issue a token on the patient’s behalf. Digital-first doesn’t have to mean digital-only.
ABHA linkage feels like extra work at a busy desk
Build it into the same check-in flow as joining the queue, so it’s one prompt, not a separate errand.
Consent text copied from a generic template
A generic “I agree” box may not meet the DPDP Act’s standard of free, specific, informed and unambiguous consent. Have your compliance or legal team review the actual notice patients see.
Doctors resist visible wait-time data
Frame the data around patient flow and staffing, not individual doctor speed, and involve clinical leadership in how it’s used before rolling it out hospital-wide.
No plan for downtime
If the internet or system goes down on a busy OPD morning, you need a fallback. Keep a paper token or register process ready, and ask any vendor what happens during an outage.
Real-World Scenarios
These are illustrative scenarios based on common patterns in Indian hospital OPDs, not case studies of named institutions.
Government hospital OPD, high daily volume. A government OPD on paper tokens had no way to see that its waits were concentrated in two specialties during morning hours. With doctor-wise digital queues, administrators could see the real bottleneck and adjust which doctors covered the peak, instead of assuming the whole OPD needed more staff.
Private multi-specialty hospital, ABDM rollout. ABHA linkage was low because front-desk staff treated it as a separate, optional step during busy mornings. Folding ABHA capture into queue check-in raised linkage without adding a counter or a new step for patients.
Diagnostic and lab department. The lab shared a waiting area and a queue with OPD consultations, so a 10-minute blood draw regularly waited behind a 25-minute follow-up. Giving the lab its own queue cut lab waits without changing consultation schedules at all.
Real-World Scenarios
These are illustrative scenarios based on common patterns across hospital OPD operations in India, not case studies of named institutions.
Government hospital OPD, high daily volume. A government hospital OPD running purely on paper tokens had no way to see that its average wait, closer to the 20-minute range typical of public facilities, was concentrated in two specialties during morning hours. After introducing doctor-wise digital queuing, administrators could see the actual bottleneck by specialty and adjust which doctors saw patients during the peak window, rather than assuming the whole OPD needed more staff.
Private multi-specialty hospital, ABDM rollout. A private hospital participating in ABDM found ABHA linkage rates were low because front-desk staff treated it as a separate, optional step during a busy morning. Folding ABHA capture into the same QR check-in flow as queue joining lifted linkage rates without adding a new counter or a new step for patients.
Diagnostic and lab department. A hospital’s lab department shared a waiting area with OPD consultation patients, so a 10-minute blood draw regularly waited behind a 25-minute consultation follow-up. Giving the lab its own queue, separate from OPD consultations, shortened lab wait times without touching consultation scheduling at all.
8 Features to Look for in a Hospital Queue Management System
When you evaluate a queue management system in hospital OPDs, doctor-wise routing and proper consent capture matter most, because a generic retail queue tool is least likely to handle them well for a hospital.

| Feature | What it does | Why it matters | Look for |
| Doctor and department routing | Sorts patients into the right sub-queue | Quick visits don’t wait behind long ones | Separate queues per doctor or department |
| Walk-ins and appointments together | Merges booked and walk-in patients | One true order for each doctor | Both visible in one dashboard |
| ABHA-ready check-in | Captures or verifies ABHA ID at check-in | Supports ABDM and DHIS | Inline prompt or HIS integration |
| Consent capture | Shows and logs a data notice | DPDP Act compliance | A visible, logged consent step |
| Live wait display | Shows the token being served per department | Lowers how long a wait feels | Works on existing TVs |
| Phone notifications | Alerts patients as their turn nears | Frees patients from crowded corridors | Browser, SMS or WhatsApp alerts; timing per department |
| Patient flow analytics | Reports waits, volume and no-shows | Turns complaints into data | Department and doctor-level detail, exportable |
| IST support and multi-branch view | Same-timezone help; one view across sites | Fast fixes during OPD peaks; comparison across branches | A stated support window and role-based access |
How Promptier Works for Hospitals and Clinics
Promptier is a QR-based queue management system in hospital OPDs and clinics that runs on the phones, laptops and screens you already have. There’s no hardware to buy, and most clinics go live the same day.
- QR check-in with no app. Patients scan a QR code and join the queue in their phone browser.
- Walk-ins and appointments in one dashboard. Booked and walk-in patients sit in one view, so each doctor’s queue is in the right order.
- Separate queues by doctor or department. Set up OPD, pharmacy, lab and billing as their own queues.
- Live position and estimated wait. Patients see where they stand and are notified on their phone as their turn approaches.
- Lobby TV display. Open a URL on any smart TV or monitor to show the token being served.
- Timestamped records. Every entry is logged, and wait-time data can be exported for audits and reviews.
- Pricing. Free to start. Pro is ₹499 per month per location. Enterprise pricing for hospital groups is custom.
If you need ABHA capture or integration with your hospital information system (HIS), ask about it in your demo, as these aren’t listed on the product page yet.
See how Promptier’s hospital queue management system works
Future Trends
- ABDM integration becoming expected. As ABDM adoption grows, hospitals that already fold ABHA linkage into check-in will be ahead of those treating it as a separate project.
- Clearer DPDP guidance for patient data. As the 18-month DPDP Rules rollout continues, expect clearer standards on consent and notice for healthcare data.
- Wait prediction from visit history. With enough logged visits, systems can forecast OPD waits by doctor and time of day, which helps both patient messaging and staffing.
Frequently Asked Questions
What is a queue management system in a hospital?
A queue management system in hospital OPDs is software that lets patients check in by QR code, kiosk or appointment and places them in the right queue: a specific doctor’s OPD, pharmacy, lab or billing. It shows their live position and wait, alerts them when their turn is near, and logs each stage of the visit instead of relying on paper tokens.
How long do patients wait in Indian hospital OPDs?
It varies widely. One study of 30 hospitals in Nellore, Andhra Pradesh, found average OPD waits of 20.3 minutes in government hospitals, 15.5 minutes in private hospitals and 39.71 minutes in voluntary-sector hospitals, with women waiting longer than men. Waits in large city hospitals can be much longer, which is why hospitals need their own logged data.
How much does a hospital queue management system cost in India?
Costs range from free starter plans to custom enterprise contracts. Promptier is free to start, its Pro plan costs ₹499 per month per location, and hospital groups get custom Enterprise pricing. Hardware-based token systems cost more upfront because they need dispensers, displays and servicing.
Is patient data collected by a hospital queue system covered by the DPDP Act?
Yes. A patient’s name, phone number and visit timestamp are personal data under the DPDP Act, 2023. The hospital collecting them is a data fiduciary with notice and consent duties. The DPDP Rules were notified on 14 November 2025 with an 18-month phased rollout. This is general information, not legal advice.
Can a queue system help with ABDM and ABHA linkage?
Yes, if it’s designed to. A queue system can prompt for or verify a patient’s ABHA ID at the same moment they check in. ABHA-linked records can count towards ABDM’s Digital Health Incentive Scheme, but the scheme is run by the National Health Authority and its rates change often, so check the current terms.
Does a queue management system replace the registration desk?
No. Most hospitals keep a staffed registration desk or kiosk alongside QR check-in, both for patients who can’t or don’t want to use a phone and as a fallback if the system or internet is down.
How is a hospital queue system different from a bank or retail queue system?
A hospital visit chains several queues together: registration, doctor-wise OPD, pharmacy, lab and billing. A hospital queue system needs routing by doctor and department, handling of walk-ins alongside appointments, and more careful handling of patient data than a typical retail queue.
What is the biggest mistake hospitals make with queue management software?
Digitising only the front desk. Registration gets faster, but pharmacy, lab and billing stay on paper, so the bottleneck simply moves and the patient’s total visit time barely changes.
Conclusion
A queue management system in hospital OPDs has to do more than replace a paper token. It has to route patients across a chain of departments, make a measurable dent in waits that research shows are long and uneven, and treat check-in as what it now is: the moment for consent and, where ABDM applies, ABHA linkage.
A faster front desk feels like progress. But if pharmacy, lab and billing stay on paper, the patient’s visit barely gets shorter. The hospitals getting real results treat this as a whole-journey project, not a registration-desk upgrade.
When you compare options, look closely at doctor-wise routing, how consent and ABHA are handled at check-in, and whether the reporting shows you wait-time gaps you didn’t know about.
See it work in your OPD. Explore Promptier’s hospital queue management system and book a free demo. No app for patients, no new hardware, support in IST hours.
Related reading
