Ask any hospital administrator in India what happens between a patient walking in and a patient seeing a doctor, and “queue” undersells it. There’s a registration line, a doctor-wise OPD queue, a pharmacy queue, a lab queue, and a billing queue — often four or five separate waits stitched into one visit, most of them still run on paper tokens or a register. Research on Indian outpatient departments has found average waiting times ranging from about 15.5 minutes in private hospitals to nearly 40 minutes in voluntary-sector hospitals, with real disparities by gender and mode of arrival that a paper token system has no way to even measure, let alone fix.
At the same time, 2026 is the year hospital check-in stopped being just an operational question. The Ayushman Bharat Digital Mission (ABDM) is pushing hospitals toward ABHA-linked patient records, and the Digital Health Incentive Scheme pays hospitals roughly ₹20 for every OPD registration linked to a patient’s ABHA ID — which means the front-desk or QR check-in moment, the same moment a patient joins the queue, is now also a compliance and incentive moment. And because that check-in step collects a patient’s name, phone number, and visit details, it’s processing personal data under the DPDP Act, 2023, whether the hospital’s queue system was built with that in mind or not.
This guide covers what a queue management system in a hospital actually needs to do: route patients across departments correctly, cut real wait time (not just claimed wait time), handle patient data the way Indian law expects, and — where a hospital chooses to — make the check-in step do double duty for ABHA linkage.
Key Takeaways
- A hospital queue is really several linked queues — registration, doctor-wise OPD, pharmacy, lab, billing — and a queue system needs to route patients across all of them, not manage one line.
- Indian OPD research has measured average waits from 15.5 minutes (private hospitals) to nearly 40 minutes (voluntary-sector hospitals), with a documented gender gap — women had roughly 19% longer median waits than men after adjusting for other factors.
- ABDM’s Digital Health Incentive Scheme pays hospitals about ₹20 per OPD registration linked to a patient’s ABHA ID — turning the check-in step into a revenue and compliance moment, not just a comfort feature.
- A patient’s name, phone number, and visit timestamp collected at queue check-in are personal data under the DPDP Act, 2023 — consent and notice obligations apply the same way they would for any other business.
- The biggest wait-time win usually isn’t a faster doctor — it’s routing patients so a 5-minute pharmacy pickup doesn’t sit behind a 20-minute consultation in the same line.
What Is a Queue Management System in a Hospital?
A queue management system in a hospital is software that lets patients check in digitally (by QR code, kiosk, or pre-booked appointment), routes them into the correct department queue — OPD by doctor, pharmacy, lab, or billing — tracks real-time wait, and logs each stage of the visit for hospital records and reporting.
A retail or bank queue only has to manage one kind of wait. A hospital visit is a chain of them: a patient might register, wait for a specific doctor’s OPD slot, walk to the pharmacy, wait again, then queue at billing — four separate waits that a single “take a token” system can’t represent at all. A hospital-appropriate queue system needs department and doctor-wise routing built in from the start, so a patient’s position in the pharmacy queue isn’t tied to when they arrived at the hospital, but to when they actually reach that counter.
The other piece that’s specific to healthcare is the record. Every check-in captures a patient’s name and phone number at minimum, and increasingly a link to their ABHA health ID. That record needs to be accurate, timestamped, and collected with proper notice — both because hospitals are held to a high standard on patient data generally, and because DPDP Act obligations apply the moment that data is collected digitally.
Key definitions you’ll see throughout this guide:
Department/doctor-wise routing: automatically directing a patient into the correct sub-queue — a specific doctor’s OPD, pharmacy, lab, or billing — instead of one blended line.ABHA ID: the Ayushman Bharat Health Account, a 14-digit unique health identifier under ABDM that links a patient’s records across providers.DHIS: the Digital Health Incentive Scheme under ABDM, which pays participating hospitals for ABHA-linked digital health records, including OPD registrations.Personal data(DPDP Act, 2023): any data about an individual who is identifiable by or in relation to that data — a patient’s name, phone number, and visit timestamp all qualify.
The Patient Journey: Where Hospital Queue Management Actually Fits
Queue management isn’t just the moment a patient waits at a counter — it spans four stages of a hospital visit: pre-arrival (booking and expectations), arrival (check-in and consent), service (department-wise routing and care), and post-visit (billing, follow-up, and the data left behind). A system that only touches one of these stages is solving a smaller problem than it looks like it is.
Pre-arrival. Online appointment booking, pre-visit instructions, and — where a hospital participates in ABDM — advance ABHA linkage all happen here. A patient who arrives already registered has a fundamentally different check-in experience than a first-time walk-in.
Arrival. The check-in moment itself: QR code, kiosk, or front-desk registration. This is also where consent for data use should be captured, and where a patient’s expectations for the visit get set with a realistic wait estimate instead of silence.
Service. The stage most people picture when they hear “queue management” — doctor-wise OPD, pharmacy, lab, billing. This is where department routing, live wait visibility, and staff call-up matter most, and where most of this guide is focused.
Post-visit. Often left out of the conversation entirely, but this is where billing queues, prescription pickup, and follow-up appointment booking happen — and where the visit’s data (wait times, no-shows, service durations) becomes something a hospital can actually analyze instead of losing to a paper register.
Treating queue management as one stage in a four-stage journey, rather than a single line at a single counter, is what separates a system that improves front-desk optics from one that measurably shortens a patient’s total time in the building.
Why This Matters for Hospitals in India Right Now
Three things are converging on hospital front-desk operations in 2026: real (not anecdotal) evidence that OPD waits are long and unevenly distributed, a financial incentive under ABDM tied directly to how patients are registered, and a legal obligation under the DPDP Act to handle the data collected at check-in properly.
Start with the evidence. A study of outpatient waiting time in Indian hospitals found average waits of 20.3 minutes in government hospitals, 15.5 minutes in private hospitals, and 39.71 minutes in voluntary-sector hospitals — and, more strikingly, a consistent gender gap, with women’s median wait time about 19% longer than men’s even after adjusting for other factors. Patients arriving by ambulance waited 64% less than others in the hospitals studied, but that advantage disappeared in public-sector facilities. None of that is visible on a paper token system; it only becomes visible once check-in and wait times are actually logged.
Then there’s ABDM. Hospitals are being pushed toward ABHA-linked patient records, and the Digital Health Incentive Scheme pays roughly ₹20 per OPD registration linked to a patient’s ABHA ID, with hospitals able to earn meaningful incentive amounts through ABHA linkages and shared health records. That means the check-in step — the same moment a patient joins the queue — is where a hospital either captures that link or misses it.
Finally, the DPDP Act, 2023 applies the same way it would to any business: a patient’s name and phone number collected to run a queue system is personal data, and the hospital collecting it is acting as a data fiduciary with consent and notice obligations. This is general information, not legal advice — hospitals should have their own compliance or legal team review how patient data is actually captured and used.
📊 Key Stat: The nearly 40-minute average wait measured in voluntary-sector hospitals versus 15.5 minutes in private hospitals is not a small gap — it’s the difference between a workable OPD morning and one that visibly backs up into the parking lot. A queue system’s first job is making that gap visible by department and doctor, not guessing at it.
Key Benefits of a Hospital Queue Management System
The primary benefit is that patients spend measurably less time standing in a hallway, staff get an accurate record of every step of a visit, and the same check-in step can double as ABHA linkage and DPDP-compliant consent capture — three outcomes from one workflow change.
Shorter, more predictable waits. Routing a 5-minute pharmacy pickup away from a 20-minute consultation queue means the pharmacy patient doesn’t inherit the consultation patient’s wait — a structural fix, not a “hire more staff” fix.
A visible, defensible record of patient flow. Every check-in, department transfer, and completion is timestamped, so “how long did this patient actually wait for Dr. X” has a real answer instead of a guess.
A natural point to capture ABHA linkage. The same QR check-in that joins a patient to a queue can prompt for ABHA ID capture, supporting DHIS incentive eligibility without adding a separate administrative step.
A documented consent step for patient data. Digital check-in is a natural point to show patients what data is collected and why, and to log their consent — turning a DPDP obligation into a normal part of an existing workflow.
Real visibility into gender and access gaps. Research shows women and non-ambulance patients can wait meaningfully longer in some facilities — a queue system that logs this data is the only way a hospital can actually see and address that pattern instead of assuming it doesn’t exist.
Fewer crowded waiting areas. A patient who can wait in the parking lot or a nearby seating area instead of standing in a packed OPD corridor is both more comfortable and easier for staff to manage.
Cleaner multi-department reporting. Administrators can see OPD, pharmacy, lab, and billing wait times separately instead of one blended average that hides where the real bottleneck is.
Real relief for front-desk and clinical staff, not just patients. Staff spend less time fielding “how much longer” questions and re-explaining delays — a daily friction reduction that’s real even though it’s harder to put a single number on than a headline wait-time claim.
A defensible ROI story instead of an unlabeled percentage. A lot of global vendor content cites impressive-sounding numbers — wait time cut from two hours to fifteen minutes, “up to 30%” productivity gains — without saying which hospital, what specialty, or how it was measured. This guide leans on independently published Indian OPD research instead, because a number you can trace to a study is worth more to a buying decision than a number you can’t.

| Dimension | Manual Token / Register | Digital Hospital Queue |
|---|---|---|
| Department routing | One line per counter, manually managed | OPD/pharmacy/lab/billing routed automatically |
| Wait-time visibility | Anecdotal, department by department | Logged and comparable across departments |
| ABHA linkage | A separate administrative step, if done at all | Captured at the same check-in moment |
| Consent for patient data | Not collected | Captured at check-in, logged |
| Equity visibility | Invisible | Measurable (e.g., wait time by patient group) |
| ROI evidence | Anecdotal or unsourced vendor claims | Grounded in independently published research |
💡 Pro Tip: If your OPD can only fix one thing first, fix doctor-wise routing before anything else. It’s the change most likely to show up as a real, measurable drop in average wait — before you touch consent flows or ABHA integration.
How It Works: The Hospital Queue Journey
A hospital-appropriate queue system runs a four-stage flow: a patient checks in (QR code, kiosk, or pre-booked appointment, with optional ABHA capture), the system routes them into the right department queue, they wait with a live position and consented SMS updates, and each stage is logged when completed.
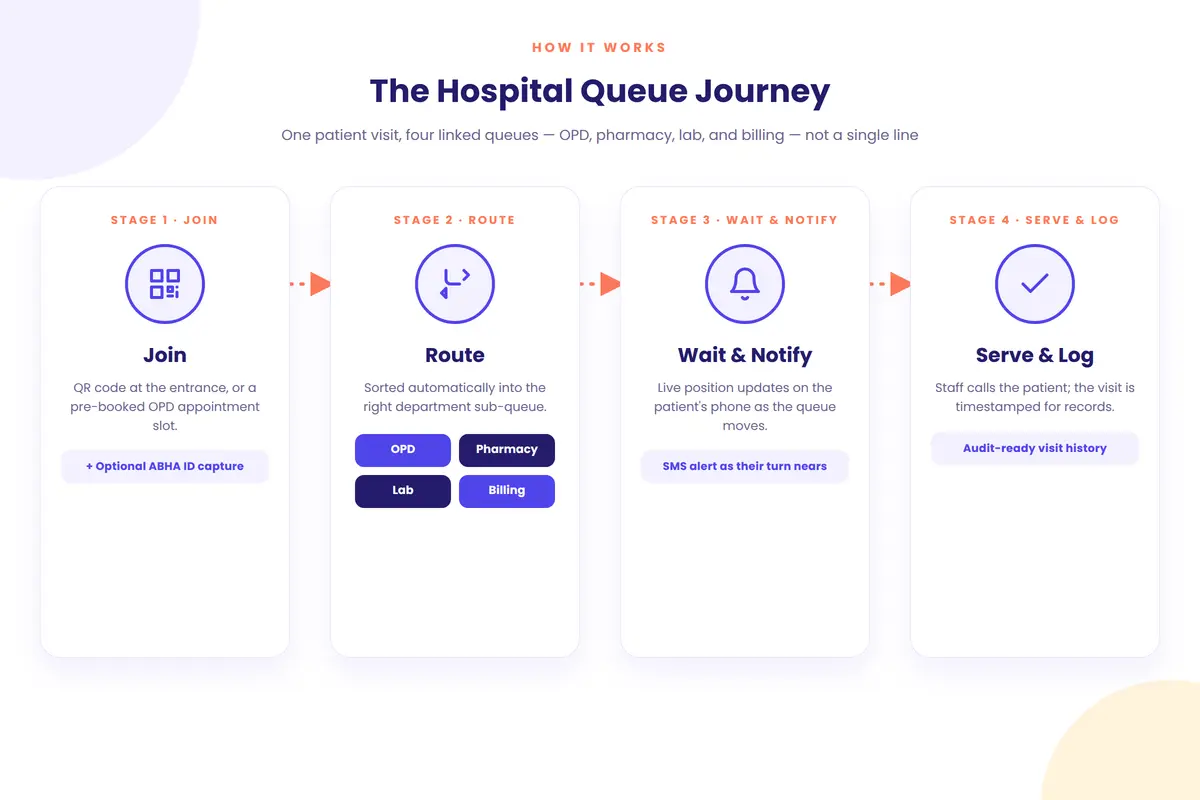
Stage 1: Join
Input: A walk-in patient at registration, or a patient who pre-booked an OPD appointment online.
Process: The patient scans a QR code or checks in at a kiosk, is shown a clear consent notice for SMS/data use, and — where the hospital participates in ABDM — is prompted to link or verify their ABHA ID.
Output: A queue ticket with a position, an estimated wait, a logged consent record, and (optionally) an ABHA-linked registration.
Stage 2: Route
Input: The patient’s stated purpose — a specific doctor’s OPD, pharmacy pickup, lab test, or billing.
Process: The system places the patient into the correct department sub-queue instead of one blended line.
Output: A correctly-ordered queue per doctor or department, instead of one line covering every kind of visit.
Stage 3: Wait & Notify
Input: The patient’s live position within their department queue.
Process: Position and estimated wait update continuously; an SMS notification fires as their turn nears, so patients aren’t stuck standing in a corridor.
Output: A patient who returns to the right counter right as their turn arrives, and a waiting area that isn’t overcrowded.
Stage 4: Serve & Log
Input: The patient’s arrival at the counter or consultation room, and the staff member or doctor assigned.
Process: Staff calls the patient, the visit stage is completed, and the system logs the full timeline — check-in time, department, wait duration, and completion time.
Output: A timestamped record that feeds both the hospital’s operational dashboard and (where relevant) ABDM/DHIS reporting.
| Stage | Cadence | Owner | Typical Tooling |
|---|---|---|---|
| Join | Continuous | Patient (self-service) or front desk | QR code, kiosk, booking link, consent notice |
| Route | Automated | System | Doctor/department sub-queues |
| Wait & Notify | Continuous | System | Live position, SMS alert |
| Serve & Log | Per visit | Staff/doctor | Counter or room call-up, timestamped record |
Best Practices for Hospital Queue Management
The single most impactful practice is routing by doctor and department before optimizing anything else — most of the wait-time gap in Indian OPD research traces back to blended queues, not slow individual service.
Route by doctor, not just by department. Before: one OPD line for every doctor in a specialty. After: each doctor has a visible sub-queue, so patients can see a realistic wait tied to the specific doctor they’re seeing.
Separate quick transactions from long ones. Before: a 5-minute pharmacy pickup waits behind a 20-minute consultation follow-up in one shared line. After: pharmacy, lab, and billing each get their own queue.
Capture ABHA linkage at check-in, not as an afterthought. Before: ABHA linkage is a separate desk or process patients often skip. After: it’s offered at the same QR check-in moment as joining the queue, supporting DHIS incentive eligibility without extra patient effort.
Make consent part of check-in, not implied. Before: a phone number collected with no record of consent. After: a clear, logged consent step built into digital check-in.
Track wait time by patient group, not just overall. Before: one average wait time hides real gaps. After: administrators can see if certain patient groups are waiting meaningfully longer, and investigate why.
Review department-level data on a fixed schedule. Before: wait-time complaints are the only signal anyone acts on. After: a weekly look at OPD, pharmacy, lab, and billing wait times catches a building problem before it becomes a complaint pattern.
⚠️ Watch Out: The most common mistake isn’t picking the wrong queue software — it’s rolling it out only at the main registration desk and leaving pharmacy, lab, and billing on paper. The consultation might get faster while the patient’s total visit time barely changes, because the bottleneck just moved downstream.
| Condition | Recommended Action | Expected Outcome |
|---|---|---|
| One blended OPD line for multiple doctors | Route by individual doctor | Patients see a realistic, doctor-specific wait |
| Quick transactions (pharmacy, billing) stuck behind long ones | Give each department its own queue | Total visit time drops without adding staff |
| ABHA linkage handled as a separate step | Offer it at the same check-in moment as queue join | Higher ABHA linkage rate, DHIS incentive support |
| No visibility into wait-time gaps by patient group | Track and review wait time by group | Equity issues become visible and addressable |
Common Challenges and How to Solve Them
The most common challenge is treating the front desk as the only place that needs a digital queue, while pharmacy, lab, and billing stay on paper — which means the total patient visit time barely improves even after registration gets faster.
Challenge: Only Registration Gets Digitized
Hospitals often start (and stop) with a digital token at the main desk, leaving downstream departments unchanged. Solution: roll out department-level queues in phases, but commit to covering pharmacy, lab, and billing within a defined timeline, not indefinitely.
Challenge: Elderly or Less Digitally-Comfortable Patients Struggle with QR Check-In
Not every patient can or wants to use a phone to join a queue. Solution: keep a staffed kiosk or front-desk option alongside QR check-in — digital-first doesn’t have to mean digital-only.
Challenge: ABHA Linkage Feels Like Extra Work at a Busy Desk
Front-desk staff under time pressure may skip offering ABHA linkage even when the queue system supports it. Solution: build it into the same check-in flow as queue joining, so it’s a checkbox, not a separate errand.
Challenge: Consent Language Gets Copied From a Generic Template
A generic “I agree” checkbox may not meet the DPDP Act’s standard for clear, informed, affirmative consent, and healthcare data warrants particular care. Solution: have the hospital’s compliance or legal function review the actual consent notice shown at check-in.
Challenge: Doctors Resist Visible Wait-Time Data
A doctor may see published wait-time data as a personal performance metric rather than an operational signal. Solution: frame department-level data around patient flow and staffing decisions, not individual doctor speed, and involve clinical leadership in how the data is used.
Real-World Scenarios
These are illustrative scenarios based on common patterns across hospital OPD operations in India, not case studies of named institutions.
Government hospital OPD, high daily volume. A government hospital OPD running purely on paper tokens had no way to see that its average wait, closer to the 20-minute range typical of public facilities, was concentrated in two specialties during morning hours. After introducing doctor-wise digital queuing, administrators could see the actual bottleneck by specialty and adjust which doctors saw patients during the peak window, rather than assuming the whole OPD needed more staff.
Private multi-specialty hospital, ABDM rollout. A private hospital participating in ABDM found ABHA linkage rates were low because front-desk staff treated it as a separate, optional step during a busy morning. Folding ABHA capture into the same QR check-in flow as queue joining lifted linkage rates without adding a new counter or a new step for patients.
Diagnostic and lab department. A hospital’s lab department shared a waiting area with OPD consultation patients, so a 10-minute blood draw regularly waited behind a 25-minute consultation follow-up. Giving the lab its own queue, separate from OPD consultations, shortened lab wait times without touching consultation scheduling at all.
💡 Pro Tip: In each scenario, the fix was structural — separate the queue by department or specialty, and fold compliance steps into the existing check-in flow — rather than simply asking staff to move faster.
8 Features to Look for in a Hospital Queue Management System
Doctor/department-wise routing and DPDP-ready consent capture matter most, because these are the two things a generic retail queue tool is least likely to handle correctly for a hospital.
Doctor and department-wise routing. Definition: automatically sorting patients into the correct doctor’s OPD, pharmacy, lab, or billing sub-queue. Why it matters: prevents quick transactions from waiting behind long consultations. Look for: configurable routing per doctor or department, not just per counter.
ABHA-ready check-in. Definition: the ability to prompt for or verify a patient’s ABHA ID at the same moment they join the queue. Why it matters: supports DHIS incentive eligibility without a separate administrative step. Look for: check-in flows that can capture or link ABHA ID inline.
DPDP-ready consent capture. Definition: a check-in step that records clear, affirmative consent for SMS/data use. Why it matters: patient data carries particular sensitivity, and a logged consent record is real protection, not just a checkbox. Look for: a visible, logged consent notice at check-in.
Real-time wait display. Definition: a lobby or waiting-area screen showing live queue status per department. Why it matters: visible progress reduces how long a wait feels, even when the actual wait doesn’t change. Look for: displays that work on existing TVs or tablets.
SMS notifications. Definition: automated alerts as a patient’s turn nears. Why it matters: lets patients wait outside a crowded corridor and return on time. Look for: configurable timing per department (a pharmacy alert and an OPD alert don’t need the same lead time).
Patient flow analytics. Definition: reporting on wait time, volume, and no-show rate by department and doctor. Why it matters: turns anecdotal complaints into an actual operational signal. Look for: reporting granular enough to separate departments, not one blended average.
Multi-branch dashboard for hospital chains. Definition: one view across multiple hospital locations. Why it matters: lets a chain compare OPD performance across facilities. Look for: role-based access so facility and group-level staff see what’s relevant to them.
IST business-hours support. Definition: vendor support available during Indian business hours. Why it matters: a queue system going down during a busy OPD morning needs a fast, same-timezone response. Look for: a stated support SLA in IST.

| Feature | What It Does | Why It Matters for Hospitals | Look For |
|---|---|---|---|
| Doctor/department routing | Sorts patients into correct sub-queues | Prevents quick visits waiting behind long ones | Configurable per doctor/department |
| ABHA-ready check-in | Captures/links ABHA ID at join | Supports DHIS incentive eligibility | Inline capture, no separate step |
| DPDP-ready consent | Logs clear consent at check-in | Lawful processing of patient data | Visible, logged consent notice |
| Real-time wait display | Shows live queue status publicly | Lowers perceived wait time | Works on existing screens |
| SMS notifications | Alerts patients as turn nears | Frees patients from crowded corridors | Configurable per department |
| Patient flow analytics | Reports wait/volume/no-shows | Turns complaints into operational data | Department-level granularity |
| Multi-branch dashboard | One view across hospital locations | Cross-facility comparison | Role-based access |
| IST business-hours support | Same-timezone vendor support | Fast response during OPD peak hours | A stated support SLA |
Risks and Pitfalls
The highest-severity risk is digitizing the front desk while leaving downstream departments on paper — patients notice a faster check-in but not a shorter total visit, and the project gets blamed for not working.
Digitizing only the entry point. A faster registration step doesn’t help if pharmacy, lab, and billing are still unmanaged lines. Plan department coverage from the start, even if rollout is phased.
Treating ABHA linkage as separate from queue check-in. Two different steps at two different counters means lower linkage rates and more patient friction than folding it into one flow.
Weak consent language. A checkbox that exists but doesn’t meet the DPDP Act’s standard for clear, informed, affirmative consent offers limited real protection — have the actual notice text reviewed, not just its presence.
No accommodation for patients who can’t use a phone. A digital-only check-in excludes elderly or less digitally-comfortable patients. Keep a staffed alternative available.
No offline fallback. A hospital that can’t check in a single patient when the system or network goes down has a real operational risk during a busy OPD morning. Confirm what happens during downtime before committing to a vendor.
⚠️ Watch Out: Publishing wait-time data without clinical leadership buy-in can turn a useful operational tool into a source of friction with doctors. Involve clinical stakeholders in how department-level data is framed and used before rolling it out hospital-wide.
Future Trends
The clearest near-term trend is ABDM integration moving from optional to expected, with the check-in/queue moment becoming the natural point where ABHA linkage, consent, and patient flow all happen together.
ABDM integration becoming standard practice. As DHIS incentives and broader ABDM adoption continue, hospitals that already fold ABHA linkage into check-in will have a real head start over those treating it as a separate administrative project.
DPDP Rules enforcement maturing for healthcare data. As DPDP Rules, 2025 implementation continues, expect clearer guidance on consent and notice standards specifically relevant to patient data — reducing ambiguity for hospitals building or buying queue systems today.
AI-assisted wait prediction by doctor and department. As hospitals accumulate visit history, predictive models can forecast OPD wait by doctor and time of day, useful for both patient communication and staffing decisions.
Queue and patient-flow data feeding staffing decisions directly. Rather than administrators manually reviewing reports, patient-flow data is starting to connect directly to staffing and scheduling tools, suggesting where a second doctor or counter is needed based on the same data the queue system already collects.
Frequently Asked Questions
What is a queue management system in a hospital?
It’s software that lets patients check in digitally — by QR code, kiosk, or pre-booked appointment — and routes them into the correct department queue (a specific doctor’s OPD, pharmacy, lab, or billing), tracking wait time and logging each stage of the visit instead of relying on a single paper token line.
How long do patients typically wait in Indian hospital OPDs?
Research on outpatient waiting time in Indian hospitals found average waits of about 20.3 minutes in government hospitals, 15.5 minutes in private hospitals, and 39.71 minutes in voluntary-sector hospitals, with waits varying further by gender and mode of arrival.
Is patient data collected by a hospital queue system covered by the DPDP Act?
Yes. A patient’s name, phone number, and visit timestamp are personal data under the DPDP Act, 2023, because they identify an individual. A hospital collecting this to run a queue system takes on data fiduciary obligations, including proper notice and consent. This is general information, not legal advice.
Can a queue system help with ABDM and ABHA ID linkage?
Yes, when designed to. A queue system can prompt for or verify a patient’s ABHA ID at the same check-in moment they join the queue, which supports ABDM’s Digital Health Incentive Scheme (DHIS), under which hospitals receive an incentive for ABHA-linked OPD registrations — though the incentive scheme itself is administered by ABDM, not by the queue software.
Does a queue management system replace the hospital’s registration desk?
No — most hospitals keep a staffed registration or kiosk option alongside digital QR check-in, both for patients who can’t or don’t want to use a phone and as a fallback if the digital system is unavailable.
How is hospital queue management different from a retail or bank queue system?
A hospital visit typically chains together several separate queues — registration, doctor-wise OPD, pharmacy, lab, billing — so the system needs department and doctor-level routing, not just one line, along with more careful handling of patient data than a typical retail queue app.
What’s the biggest mistake hospitals make when adopting queue management software?
Digitizing only the front desk and leaving pharmacy, lab, and billing on paper. Registration gets faster, but the patient’s total visit time barely changes because the bottleneck simply moves to whichever department is still unmanaged.
Is a “queue management system” the same as a “patient journey management system”?
Not quite, though the terms overlap. “Queue management” usually refers narrowly to the check-in-to-service stage — joining a line and being called. “Patient journey management” is a broader framing that also includes pre-arrival booking and post-visit steps like billing and follow-up. In practice, the systems worth evaluating today cover both, since a queue is only one stage of a much longer visit.
Conclusion
A queue management system in a hospital has to do more than replace a paper token — it has to route patients across a chain of departments, make a documented dent in wait times that real research shows are long and unevenly distributed, and handle the check-in moment as what it actually is now: a compliance step, a consent step, and — where ABDM applies — an ABHA linkage step, all at once.
The tension worth naming honestly: a faster front desk feels like progress, but if pharmacy, lab, and billing stay on paper, the patient’s actual visit barely gets shorter. The hospitals getting real results are the ones treating this as a full patient-journey project, not a registration-desk upgrade.
If you’re evaluating queue management options for a hospital or clinic network in India, look closely at department-level routing, how ABHA and consent are handled at check-in, and whether the reporting can show you wait-time gaps you didn’t know existed — explore how Promptier is built around exactly those requirements for Indian healthcare operations.
